
Tennis Elbow & Forearm Tendinopathy
Evidence-based lateral epicondylalgia rehabilitation, tendon load optimization, and functional grip restoration with Dr. Waheed Muhammad in Swabi.

What causes tennis elbow (lateral epicondylalgia)?
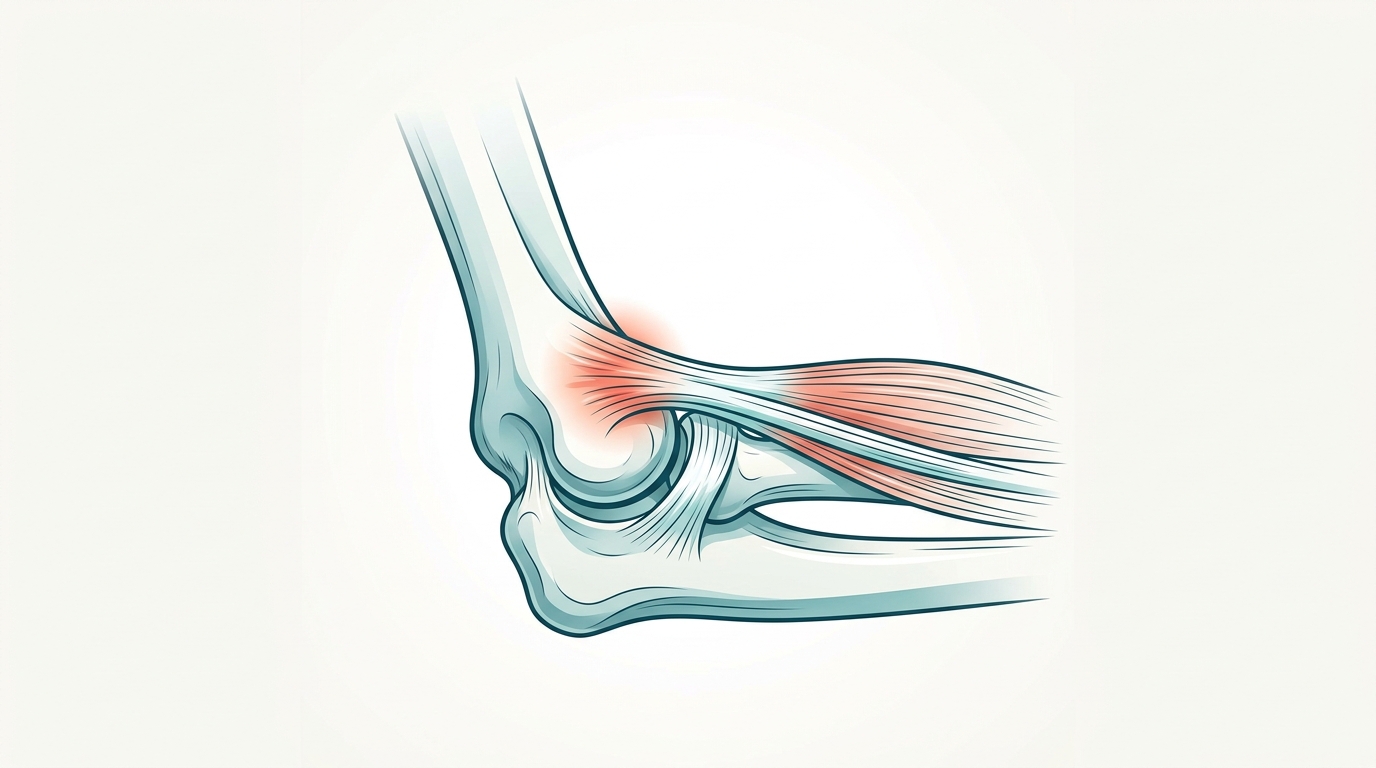
Tennis elbow, medically termed lateral epicondylalgia or common extensor tendinopathy, is a degenerative overload condition affecting the tendon attachment on the outer bony bump of the elbow. Despite its inflammatory-sounding suffix (-itis), current histologic research confirms it is primarily a tendinosis: a failed collagen healing response marked by disorganized tendon fibers, hypervascularity, and hyper-sensitized local nociceptors.
The primary structure involved is the extensor carpi radialis brevis (ECRB) tendon. Because this muscle works continuously during gripping to stabilize the wrist in extension, repeated gripping, keyboarding, plumbing, typing, or racket sports place constant tensile and friction stress across its bone-tendon junction.
Complete rest or repeated cortisone injections often fail to cure the condition because tendons require progressive mechanical tension to realign collagen fibers and rebuild load capacity.
Key signs and functional symptoms of lateral epicondylalgia
Lateral Epicondyle Tenderness
Sharp, localized tenderness 1 to 2 cm distal to the outer elbow bone, aggravated by direct touch or contact with hard surfaces.
Weakened, Painful Grip
Sharp discomfort or sudden loss of grip strength when lifting a kettle, pouring tea, carrying shopping bags, or shaking hands.
Pain with Resisted Extension
Provocation of deep lateral elbow pain when backward bending the wrist or extending the middle finger against resistance.
Forearm Muscle Tightness
Morning stiffness and dull aching along the posterior forearm muscles, easing slightly with gentle warmth and gentle motion.
When to seek urgent medical evaluation (Red Flags)
While lateral epicondylalgia is usually benign, seek prompt specialist consultation if you experience: sudden elbow lock or inability to straighten the joint after a fall; gross elbow swelling, heat, or systemic fever (septic bursitis); or severe numbness, tingling, and motor weakness radiating into the fingers (requiring differential evaluation for cervical radiculopathy or radial tunnel entrapment).
How physiotherapy restores tendon capacity and grip

Phase 1: Pain Modulation & Isometric Loading: In the irritable stage, we introduce sustained isometric wrist extension holds. Isometrics reduce cortical tendon inhibition, induce immediate analgesia, and maintain motor unit recruitment without causing compressive tendon irritation.
Phase 2: Heavy Slow Resistance & Eccentric Remodeling: Once pain stabilizes, we progress to heavy slow resistance (HSR) and eccentric loading (such as the Tyler Twist technique with resistance bars and dumbbells). Eccentric loading applies mechanical strain to tenocytes, stimulating protein synthesis and laying down organized type I collagen.
Phase 3: Kinetic Chain & Ergonomic Optimization: Elbow overload frequently stems from weak scapular stabilizers or impaired rotator cuff mechanics. We retrain shoulder girdle control, optimize workstation ergonomics, and coach tool-handling biomechanics to prevent recurrence.
What to expect during tennis elbow rehabilitation
Phased Recovery Roadmap
Weeks 1–3 (Pain Settling): Ergonomic modification, counterforce bracing if indicated, and daily analgesic isometric holds.
Weeks 4–8 (Tendon Capacity Building): Heavy slow resistance, eccentric wrist extension, and progressive grip strengthening.
Weeks 8–16+ (Functional Return): Scapular kinetic chain integration, sport-specific or trade-specific drills, and long-term resilience.
Do I have to play tennis to develop tennis elbow?
No. Over 90% of individuals diagnosed with lateral epicondylalgia do not play tennis. It is most prevalent in individuals aged 35 to 55 who perform repetitive forearm gripping, typing, mouse work, plumbing, carpentry, or food preparation.
Should I get a cortisone injection for my elbow pain?
High-quality randomized clinical trials indicate that while corticosteroid injections provide rapid short-term pain suppression (weeks 1–6), they result in significantly higher recurrence rates and worse tendon architecture at 6 to 12 months compared to physiotherapy and progressive loading.
How long does tennis elbow take to heal completely?
With structured mechanical loading and activity modification, noticeable relief and grip improvement occur within 4 to 6 weeks. Complete collagen maturation and functional capacity typically solidify over 8 to 16 weeks.
Related upper limb & musculoskeletal care
Shoulder Pain
Subacromial impingement, rotator cuff care, and scapular stabilization.
Regain Pain-Free Grip & Arm Function
Book a personalized clinical assessment at Dr Waheed Physio in Swabi. We develop tailored load-remodeling plans to resolve elbow pain at its root.