
Spinal Cord Injury Rehabilitation & Mobility Care
Specialized neuro-rehabilitation, transfer training, and adaptive functional independence for spinal cord injury in Swabi.

Understanding spinal cord pathology, ASIA impairment, and functional potential
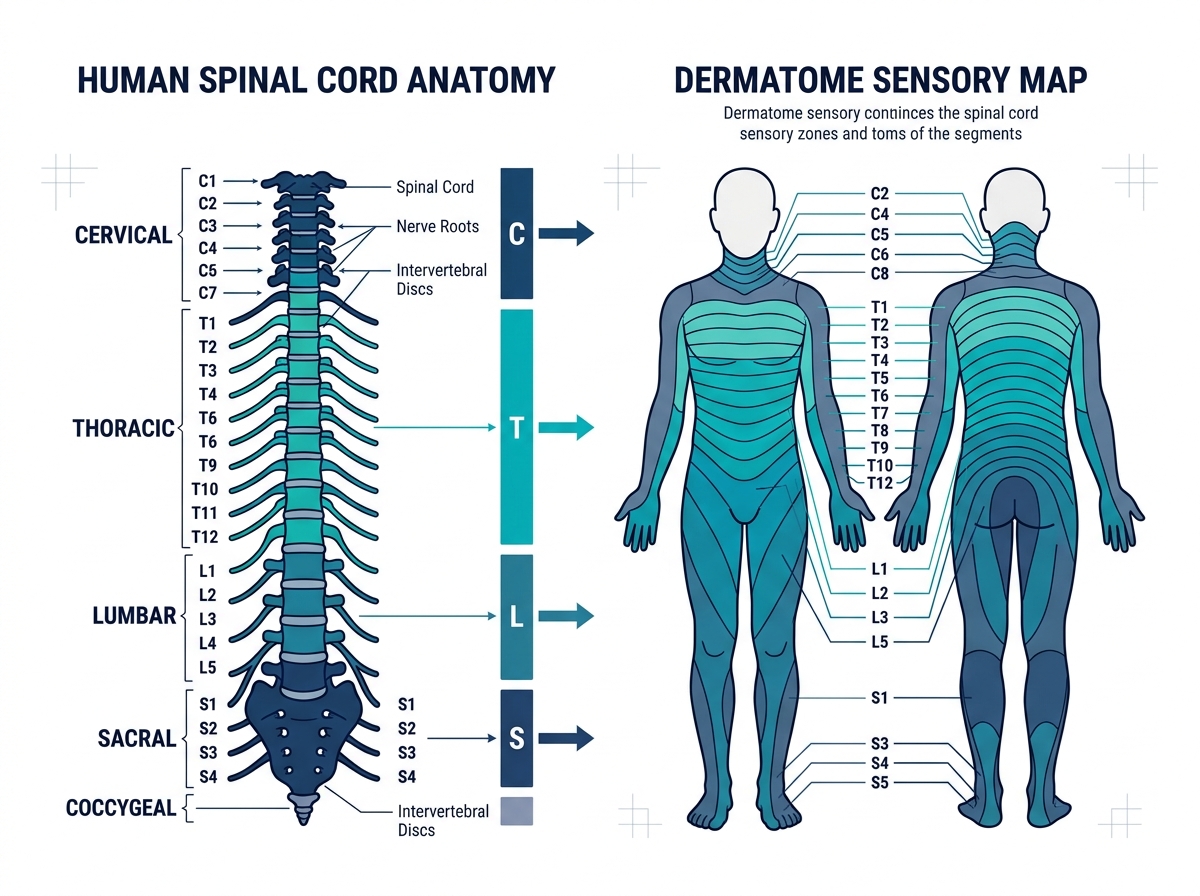
Spinal cord injury (SCI) disrupts ascending sensory and descending motor pathways between the brain and periphery. Lesions are classified by the American Spinal Injury Association (ASIA/ISNCSCI) Impairment Scale from AIS A (complete sensorimotor loss) to AIS B–D (incomplete lesions retaining sensory or motor sparing) and AIS E (normal function).
In incomplete injuries, neuroplasticity allows surviving descending axonal pathways to be re-educated through intensive, task-specific mechanical training. In complete injuries, rehabilitation focuses on compensatory functional mastery: developing hypertrophied upper limb strength, dynamic head-hips transfer mechanics, and total autonomy in wheelchair mobility.
Crucially, physical therapy addresses systemic multi-organ complications: spasticity, neuropathic pain, orthostatic hypotension, autonomic dysreflexia, contractures, heterotopic ossification, and pressure ulcer vulnerability.
Key indicators and functional symptoms
Motor & Sensory Impairment
Paresis or paralysis and altered sensation below the neurological level of injury, requiring targeted functional retraining.
Spasticity & Involuntary Clonus
Hypertonia, exaggerated deep tendon reflexes, and muscle spasms resulting from loss of descending upper motor neuron inhibition.
Impaired Sitting Balance
Loss of abdominal and trunk stabilizer innervation, demanding compensatory shoulder and latissimus balance strategies.
Autonomic Instability
Susceptibility to blood pressure swings, impaired thermal regulation, and dysreflexic episodes in injuries above T6.
When to seek urgent medical evaluation (Red Flags)
EMERGENCY ALERT — AUTONOMIC DYSREFLEXIA: In individuals with injuries at or above T6, an uninhibited sympathetic response to noxious stimuli below the lesion (distended bladder, bowel impaction, pressure ulcer) causes life-threatening severe hypertension, throbbing headache, profuse sweating above the injury, and bradycardia. Immediately sit the patient upright, loosen constrictive clothing, check urinary drainage, and seek urgent emergency medical attention.
Evidence-based neuro-rehabilitation protocols for spinal cord injury

Phase 1: Acute Management & Contracture Prevention: We emphasize passive joint range of motion, tenodesis grip preservation for cervical injuries, respiratory physiotherapy, tilt-table orthostatic reconditioning, and strict pressure-relief positioning.
Phase 2: Transfer Mastery & Wheelchair Skills: Utilizing the head-hips relationship, patients master sliding-board and depression transfers, mat mobility, wheelie balancing, and energy-efficient manual wheelchair propulsion.
Phase 3: Locomotor & Standing Retraining: For incomplete SCI, we utilize body-weight supported treadmill training, parallel bars, and progressive orthotic ambulation (KAFOs/AFOs) to stimulate spinal central pattern generators.
What to expect during rehabilitation
Spinal Cord Injury Rehabilitation Roadmap
Acute / Early Stage: Respiratory care, vital sign stabilization, contracture prevention, and wheelchair seating assessment.
Active Rehabilitation Stage: Independent transfers, dynamic wheelchair propulsion, core balance, and standing frame protocols.
Community Reintegration: Outdoor mobility, vehicle transfer independence, adaptive sport, and lifelong pressure ulcer prevention.
What is the difference between complete and incomplete spinal cord injury?
Complete injuries (AIS A) have no sensory or motor preservation in the lowest sacral segments (S4–S5). Incomplete injuries retain partial descending neural tracts, offering greater potential for motor recovery through physical therapy.
How do you prevent pressure ulcers in wheelchair users?
Prevention relies on pressure-relief cushions, performing pressure-relief push-ups or weight shifts every 15 to 20 minutes, daily skin checks with a mirror, and proper wheelchair posture.
Can a person with spinal cord injury learn to walk again?
Walking recovery depends on neurological completeness and lesion level. Incomplete injuries often regain ambulatory capacity using gait training and orthotics. For complete paraplegia, therapeutic standing maintains bone density and cardiovascular health.
Related clinical rehabilitation care
Stroke Rehabilitation
Task-oriented neuroplastic recovery and neurological gait training.
Balance & Mobility
Sensory re-weighting, assistive device training, and safe transfers.
Amputation Rehabilitation
Specialized limb conditioning and wheelchair mobility care.
Maximize Independence, Mobility & Long-Term Health
Consult ICRC-certified rehabilitation specialist Dr. Waheed Muhammad in Swabi. We structure comprehensive spinal cord injury rehabilitation plans.